
After completion of the data collection during April 2022 Ministry of Health SR for the first time carried out the calculation of the criteria for ensuring a public minimum network General outpatient care providers under the new rules adopted late 2021.
The results of the evaluation of the network status were sent to health insurance companies which may raise objections by 31 May 2022.
Ministry of Health of the Slovak Republic in terms of legislative obligation at the latest Up to 30. 30 June 2022 to publish the results of the public minimum network evaluationVAS providers.
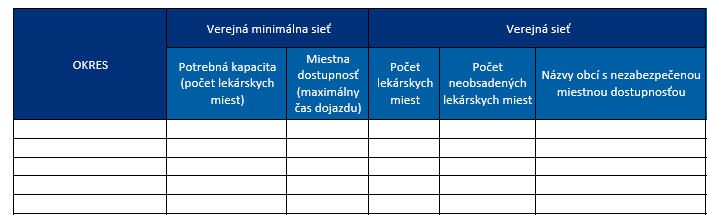
The public minimum network is newly evaluated instead of the county at district level, where for each district the basic parameters of the public minimum network are calculated (see preview in the table):
- local availability (maximum range time and municipalities with unsecured availability)
- Capacity required (number of medical places in VMS)
- Number of medical places in the public network (current number of medical places k 1.1.2022)
- Number of unoccupied medical places in the district
The results of the network state follow the classification of districtswhere each district is assigned to one of the four levels according to the degree of vulnerability health care. MZ classifies districts on the basis of three parameters:
- local availability
- Demographic structure of general practitioners (share of doctors ≥ 63 years)
- Amount of capacity needed
Maps and spreadsheets of the MZ district classification shall be published by 31 at the latest.
30 July 2022.
- missing provider code
- the different municipalities of the place of operation of the ambulance
- providers/general offices without valid database records existing authorisations issued by self-governing regions
- a general practitioner registered simultaneously as a both untested and tested physician
- a valid part-time general doctor with whom the UDZS registers Death
- general practitioners with the total sum of liabilities at level over 1,00 LM, max. 4,00 LM(429 doctors)
- doctors only with a code for specialised outpatient care and valid binding General (49 doctors)
- unregistered nurses in a chamber operating in general offices.
Problems in source data on policyholders and capitulated policyholders concerned in particular, groups:
- insured persons with unknown permanent residence in the Central Register of policyholders
- insured persons surrendering to providers without valid records in the database valid permits issued by self-governing regions
- Capitalised insured persons registered in specialist office
- Capitalised insured persons aged 30 and over registered in office general medicine for children and adolescents (2 049 capitalised policyholders).